

You’ve tried an antidepressant that didn’t work. Or a pain medication that barely touched the pain, or worse, caused a reaction nobody expected. That trial-and-error cycle has a name: pharmacogenomics (often shortened to PGx), the study of how your genes shape your response to a drug. So which medications need a PGx test before the first dose, and which only benefit from one?
For a growing list of medications, doctors don’t just guess anymore; they check first. A PGx test reads specific genes tied to how your body absorbs, breaks down, and reacts to medication, and for some drugs that check now comes before the prescription, not after a bad reaction. Here’s which medications typically call for testing first, the gene-drug interactions behind them, what the test actually looks at, and how to get one done from home.
On this page
What Is a PGx Test & When Is It Needed?
A PGx test (also called a pharmacogenetic test) looks at genes that control how your liver breaks down medication and how your body’s receptors respond to it. The result tells you and your doctor whether a standard dose is likely to work, needs adjusting, or should be swapped for a different drug entirely.
Not every medication needs this check. The FDA’s Table of Pharmacogenomic Biomarkers in Drug Labeling lists the drugs whose labels mention genetics, and the labels fall into three groups on this exact question:
- Required or necessary: The prescribing information indicates that genetic or genomic information is needed for safe or appropriate use in a specified circumstance.
- Recommended or considered: The labeling or clinical guidance supports considering genetic testing for particular patients or treatment decisions.
- Informational: The label contains pharmacogenomic information about drug response, exposure, or risk, but does not establish a requirement to test every patient.
Knowing which bucket your medication falls into is the real question behind “does this drug need genetic testing.” A blanket yes-or-no answer rarely fits.
Which Medications Need a PGx Test First?
These are some of the best-established examples of which medications need a PGx test first, or where a result on file makes the first prescription safer. Each one has either an FDA label statement or a published dosing guideline from the Clinical Pharmacogenetics Implementation Consortium (CPIC).
| Medication | Gene | What the label or guidelines say |
|---|---|---|
| Abacavir (HIV) | HLA-B*57:01 | Screen before starting; carriers are at risk of a serious hypersensitivity reaction. |
| Carbamazepine (seizures, nerve pain) | HLA-B*15:02 | Screen before starting in patients with ancestry where the variant is common, because of the risk of severe skin reactions. |
| Siponimod (multiple sclerosis) | CYP2C9 | Genotype before starting; dosing depends on the result and some genotypes should not take it. |
| Eliglustat (Gaucher disease) | CYP2D6 | Metabolizer status must be known to choose the dose. |
| Clopidogrel (heart, stroke) | CYP2C19 | Poor metabolizers activate the drug poorly; the label carries a boxed warning. |
| Codeine and tramadol (pain) | CYP2D6 | Ultrarapid metabolizers can build up dangerous levels of the active drug. |
| Warfarin (blood thinner) | CYP2C9, VKORC1 | The label includes genotype-based starting doses. |
| Azathioprine and mercaptopurine | TPMT, NUDT15 | Testing is recommended; low-activity genotypes risk severe bone-marrow suppression. |
| Citalopram and escitalopram (depression, anxiety) | CYP2C19 | Poor metabolizers need a lower dose. |
| Atomoxetine (ADHD) | CYP2D6 | Poor metabolizers reach much higher drug levels; dosing is adjusted. |
| Simvastatin (cholesterol) | SLCO1B1 | CPIC guidance to lower the dose or switch statins for reduced-function genotypes. |
RPh Labs’ PGx testing kit reports on these medications and 240+ more from a single cheek swab. See the full medication list for specifics.
Which Medications Have Important Gene-Drug Interactions?
Gene-drug interactions show up most often around four types of medication: psychiatric drugs, blood thinners, cancer or immune-suppressing drugs, and certain pain and hormone therapies. Here’s where they matter most, based on FDA labeling and current research:
- Psychiatric medications: Citalopram, fluoxetine, and paroxetine are metabolized differently depending on your CYP2D6 and CYP2C19 status, which affects both side effects and how well the dose works.
- Blood thinners: Warfarin dosing can swing widely based on CYP2C9 and VKORC1 genes, raising bleeding risk if the starting dose is off. Clopidogrel depends on CYP2C19 to become active.
- Chemotherapy and autoimmune drugs: Azathioprine, mercaptopurine, and thioguanine carry genetic warnings tied to TPMT and NUDT15, since a poor metabolizer can face severe toxicity at a standard dose.
- Hormone and pain therapies: Elagolix has a documented interaction with the SLCO1B1 transporter gene, and codeine and tramadol depend on CYP2D6.
Not every gene-drug interaction means a drug is off the table. Most mean a different starting dose, closer monitoring, or a different drug in the same class.
Drugs That Require Genetic Testing vs. Drugs Where It Helps
Only a small number of drugs that require genetic testing carry a firm instruction to test first. Abacavir, siponimod and eliglustat are good examples: the label expects the result before the prescription is written. Carbamazepine sits close to that line for patients whose ancestry puts them at higher risk.
Far more medications fall into the “recommended” or “informational” groups. Warfarin, clopidogrel, codeine, many antidepressants and several statins all have gene-drug interactions strong enough that CPIC publishes dosing guidance, even though testing is not mandatory. For these, a result already on file lets your prescriber choose the right drug and dose on day one instead of adjusting after a problem.
If you are not sure which group a medication is in, ask your pharmacist or prescriber to check the label, or look it up in the FDA table linked above. The answer tells you whether testing is expected before the first dose, recommended for some patients, or simply useful background. Either way, a result that is already on file saves time when the next prescription is written.
That’s why many people test once, before they need it. The list of drugs that require genetic testing is short, but the list where a result changes the plan is long, and your genes don’t change, so one test covers future prescriptions too.
Warfarin Genetic Testing: Why the Starting Dose Matters
Warfarin is one of the clearest cases for warfarin genetic testing. The right dose can differ several-fold between two people of the same age and weight, and a large share of that difference comes from two genes: CYP2C9, which clears the drug, and VKORC1, the target it acts on.
The warfarin label includes starting-dose ranges based on those genotypes. People with reduced CYP2C9 function or a sensitive VKORC1 variant usually need a lower dose and reach a stable level more slowly, which is exactly when bleeding risk is highest. Warfarin genetic testing gives the prescriber that information before the first tablet.
Genetics is only part of the picture. Diet, especially vitamin K intake, other medications, age, liver function and body size all change how much warfarin you need, so regular INR checks still matter. What warfarin genetic testing adds is a better first estimate, so fewer dose changes are needed early on.
Medicare has a national coverage policy for warfarin genetic testing in defined circumstances. See the insurances we accept for how coverage works with your plan.
Genetic Testing for Medications in Mental Health
Genetic testing for medications is used most often in psychiatry, where finding the right drug can otherwise take months. Many antidepressants are processed by CYP2D6 or CYP2C19, and CPIC publishes guidance for SSRIs such as citalopram, escitalopram, sertraline and paroxetine, and for tricyclics such as amitriptyline and nortriptyline.
- Poor metabolizers can reach higher drug levels and more side effects at a standard dose.
- Ultrarapid metabolizers can clear a drug so quickly that it seems not to work.
- ADHD medications such as atomoxetine also depend on CYP2D6.
Genetic testing for medications doesn’t replace a psychiatrist’s judgment, but it can rule out options your genes are likely to handle poorly. Read more in our guide to genetic testing for antidepressants.
How Do Genes Affect the Way a Medication Works?
Most of the genes involved in medication response control an enzyme family called CYP450, especially CYP2D6, CYP2C19, CYP2C9, and CYP3A4, which break drugs down in the liver. A variant can make you clear a drug too fast, too slow, or not at all. VKORC1 affects vitamin K, which changes how blood thinners work. TPMT affects how thiopurine drugs like azathioprine get cleared. HLA genes flag a risk of serious allergic-type reactions to specific drugs.
Research published in the New England Journal of Medicine estimates that genetics accounts for roughly 20% to 95% of the difference in how people respond to the same drug, depending on the medication. That wide range is exactly why a genetic test narrows down what your specific genes say, instead of relying on population averages.
Your report translates each gene into a metabolizer status: poor, intermediate, normal, rapid or ultrarapid. That status, not the raw genotype, is what your prescriber uses to pick a drug and a dose.
Does PGx Testing Use a Blood Sample or Cheek Swab?
Most direct-to-consumer PGx tests, RPh Labs included, use a simple cheek swab, not a blood draw. You rub the swab inside your cheeks at home, mail it back in a prepaid envelope, and a CLIA-certified lab does the rest. Some hospital-based panels use a blood sample instead, especially when testing happens alongside other bloodwork, but for a standalone medication-response test, a swab captures the same DNA information without a needle. If you’ve been searching for a “blood test for genotype,” a cheek swab is the more common, less invasive route most people end up choosing.
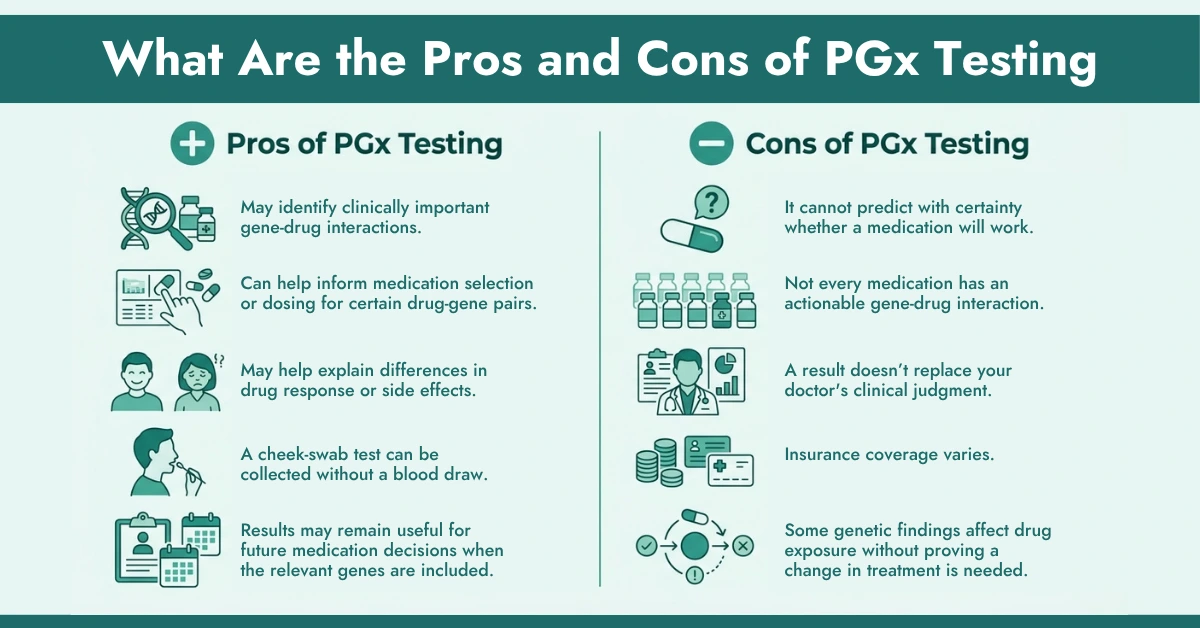
What Are the Pros and Cons of PGx Testing?
Pros of PGx Testing
- May identify clinically important gene-drug interactions.
- Can help inform medication selection or dosing for certain drug-gene pairs.
- May help explain differences in drug response or side effects.
- A cheek-swab test can be collected without a blood draw.
- Results may remain useful for future medication decisions when the relevant genes are included.
Cons of PGx Testing
- It cannot predict with certainty whether a medication will work.
- Not every medication has an actionable gene-drug interaction.
- A result doesn’t replace your doctor’s clinical judgment.
- Insurance coverage varies.
- Some genetic findings affect drug exposure without proving a change in treatment is needed.
How Does At-Home PGx Testing With RPh Labs Work?
Getting a PGx test through RPh Labs takes four steps, start to finish:
- Order online: The PGx testing kit ships to your door for $299, and it’s HSA/FSA eligible.
- Activate and swab: Register your kit through the online portal and collect the cheek swab.
- Mail it back: Use the prepaid envelope provided with your kit.
- Get your results: A CLIA-certified lab analyzes your sample, a pharmacist reviews the report, and results are posted to your secure account in 7-10 business days, covering 240+ medications.
Full details on each step are on the How It Works page, along with a 4-payment plan at 0% interest for anyone who’d rather split the cost.
Does Insurance Cover Pharmacogenetic Testing?
Coverage for pharmacogenetic testing varies by plan, so the honest answer is: sometimes. RPh Labs currently works with USA Managed Care Organization, NOVA NET, Baylor Scott & White Health Plan, Medicare, Texas Medicaid, and Blue Cross Blue Shield of Texas, though prior authorization may apply, and final eligibility comes down to your specific plan. Plans are more likely to cover the test when you take, or are about to start, a drug with known gene-drug interactions. If your insurer isn’t listed, the insurance page walks you through how to confirm coverage before you order, and self-pay is available for anyone whose plan doesn’t cover testing.
Who Should Consider PGx Testing Before Starting a Medication?
Genetic testing makes the most sense before starting a medication with a known gene interaction, or after a medication hasn’t worked the way it should.
That includes:
- Anyone starting an antidepressant or other psychiatric medication for the first time.
- Anyone who’s had a strong side effect from a standard dose of a common drug.
- Caregivers managing ADHD medications, mood stabilizers, or antidepressants for a child or dependent.
- Anyone starting warfarin, clopidogrel, or another blood thinner.
- Older adults taking several medications at once, where gene-drug interactions add up.
RPh Labs currently serves 45 states. Check the state coverage page to confirm testing is available where you live before you order.
Conclusion
If you’ve wondered which medications need a PGx test, the short answer is: a handful require it, and many more work better when your genes are known first. If a medication hasn’t worked the way you expected, or you’re about to start one with a known gene interaction, a PGx test gives you and your doctor real information instead of a guess. RPh Labs’ at-home kit checks 240+ medications from a single cheek swab, with results in 7-10 business days and a 4-payment option if you’d rather split the $299 cost.
Order your PGx testing kit or check your state’s coverage to see if RPh Labs serves your area.
Disclaimer:
This article is educational and isn’t a substitute for medical or genetic counseling advice from a licensed professional. Talk to your doctor or a genetic counselor about what your results mean for your treatment.
Frequently Asked Questions
What is a PGx test?
A PGx test (pharmacogenetic test) analyzes specific genes that affect how your body absorbs, breaks down, and responds to medication. Results show whether a standard dose is likely to work as expected, needs adjusting, or if a different medication might be a better genetic fit.
Which medications need a PGx test first?
A few drugs require it before the first dose, such as abacavir, siponimod and eliglustat, and carbamazepine for patients at higher genetic risk. Many more, including warfarin, clopidogrel, codeine and several antidepressants, have published dosing guidance where a result on file helps your prescriber choose the right drug and dose.
How accurate is genetic testing for psychiatric medications?
For the genes it tests like CYP2D6 and CYP2C19. A PGx test accurately identifies your metabolizer status. What it can’t do is guarantee a specific outcome, since mood, other medications, and non-genetic factors also shape how a psychiatric drug works for you.
Can a PGx test guarantee a medication will work for me?
No. A PGx test is one input your doctor weighs alongside your symptoms, medical history, and other medications, not a replacement for their judgment. It narrows the odds in your favor by ruling out drugs your genes are likely to react poorly to.
Is warfarin genetic testing worth it?
For many people, yes. CYP2C9 and VKORC1 explain a large share of the difference in warfarin dose between patients, and the label includes genotype-based starting doses. Medicare also covers warfarin genetic testing in defined circumstances.
How long does it take to get PGx test results?
Most people get results within 7-10 business days of the lab receiving their sample, delivered through RPh Labs’ secure online portal. You can track your kit’s status the same way.
Does RPh Labs test every state?
Not yet. RPh Labs currently serves 45 states. New York, Maryland, Pennsylvania, Rhode Island and California aren’t covered as of this writing. Check the state coverage page for the current list before you order.



Leave a Reply