

Reading about hiv symptoms in women can be reassuring or frightening depending on the day, and neither reaction tells you anything reliable. The sections below add what symptom lists cannot: how soon each test can actually detect infection, which everyday illnesses look identical, and what to do in the first 72 hours after a possible exposure.
On this page
Noticing an unexplained rash, a sore throat that won’t quit, or swollen glands can be unsettling, especially if HIV crosses your mind. HIV symptoms in women often look different from HIV symptoms in men, which makes early detection confusing for a lot of people.
Some people feel flu-like within weeks of exposure. Others notice nothing for years. This guide covers the early signs of HIV in women and men, how untreated HIV progresses to AIDS, and how doctors diagnose and treat it today, including why genetics increasingly shape which medications work best.
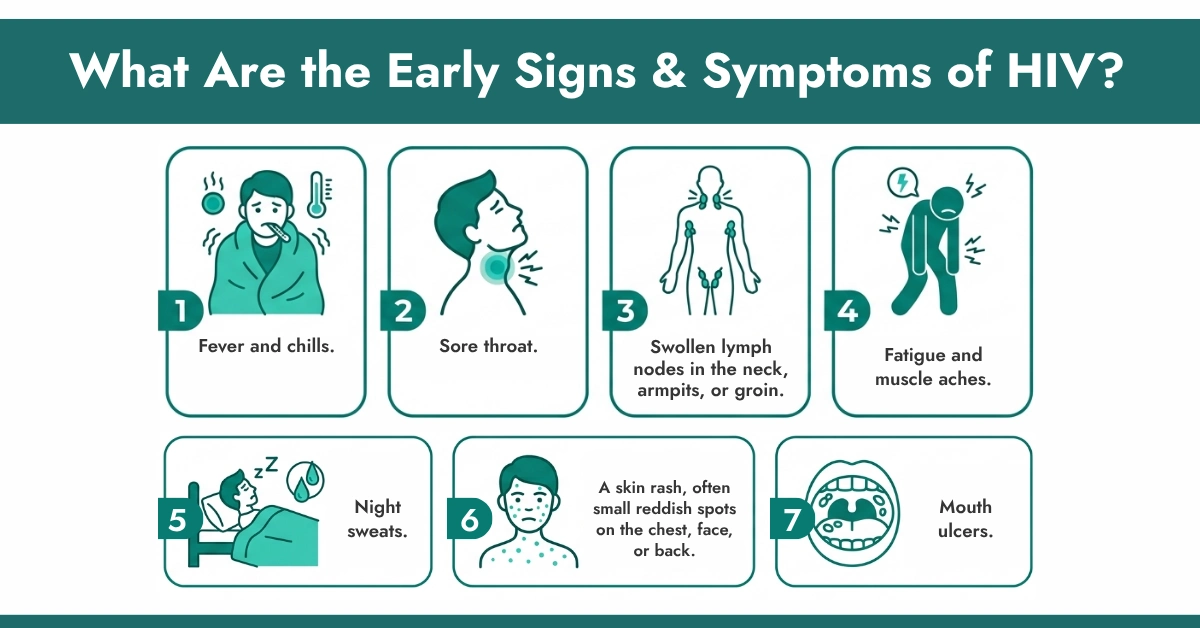
What Are the Early Signs & Symptoms of HIV?
Most early symptoms appear 2-4 weeks after exposure, a phase called acute HIV infection. The immune system’s response feels a lot like the flu.
Common early signs include:
- Fever and chills.
- Sore throat.
- Swollen lymph nodes in the neck, armpits, or groin.
- Fatigue and muscle aches.
- Night sweats.
- A skin rash, often small reddish spots on the chest, face, or back.
- Mouth ulcers.
These symptoms typically fade within one to four weeks, even without treatment. That disappearance is misleading; the virus keeps replicating quietly in the background. The CDC recommends HIV testing at least once for everyone between ages 13 and 64, regardless of symptoms. After a recent possible exposure, post-exposure prophylaxis (PEP), started within 72 hours, can still prevent infection.
What Are the Symptoms of HIV in Women?
Women experience the early signs above, plus reproductive symptoms tied to a weakened immune response.
- Vaginal yeast infections that recur several times a year or resist standard treatment
- Bacterial vaginosis that keeps coming back.
- Pelvic inflammatory disease (PID), sometimes more severe or slower to resolve than in women without HIV.
- Menstrual changes, including missed periods or heavier bleeding.
- A higher risk of HPV-related cervical changes, since HIV limits the immune system’s ability to clear the virus.
Frequent, hard-to-treat yeast infections are one of the more overlooked early indicators of HIV in women. Many people treat the infection itself and never connect it to an underlying cause.
HIV during pregnancy also requires careful management. Modern treatment can lower the risk of passing HIV to a baby to under 1%, which we cover later in this guide.
What Are the Symptoms of HIV in Men?
Men experience the same early flu-like symptoms, along with some male-specific signs.
- Genital ulcers or sores that heal slowly or recur.
- Erectile dysfunction, which is reported more often by men living with HIV than by men of the same age without it.
- Hypogonadism (low testosterone), which can cause fatigue, low libido, and reduced muscle mass.
- Proctitis, or rectal inflammation, more common among men who have sex with men.
- Painful open sores on the penis or anus.
Erectile dysfunction in men with HIV is often a hormone problem, not just stress or a medication side effect. Checking testosterone levels can uncover a treatable cause that’s easy to miss.
Persistent genital sores are also worth a doctor’s visit, since HIV and other sexually transmitted infections frequently travel together.
How Do HIV Symptoms Progress Into AIDS (Stage 3 HIV)?
Without treatment, HIV moves through three stages, defined largely by CD4 count, the immune cells the virus destroys.
| Stage | CD4 Count | What You Might Notice |
| Acute HIV | Drops sharply, then partially recovers | Flu-like symptoms for one to four weeks. |
| Chronic HIV | Often 200-499 cells/mm³, and can stay above 500 on treatment | Few or no symptoms; can last years, especially with treatment. |
| AIDS | Below 200 cells/mm³, or an AIDS-defining illness | Rapid weight loss, recurring fever, chronic diarrhea, opportunistic infections. |
AIDS is not an automatic outcome. With early antiretroviral therapy (ART), people living with HIV can live full, healthy lives and never progress to AIDS. This makes early recognition of symptoms absolutely essential.
How Is HIV Diagnosed & Treated?
- Getting Tested for HIV: HIV tests check blood or oral fluid for antibodies, antigens, or the virus’s genetic material. Most modern lab tests can detect HIV within a few weeks of exposure, though the exact window depends on the test type. A reactive result is always confirmed with a second, more specific test before diagnosis.
- Treatment With Antiretroviral Therapy (ART): There’s no cure, but ART controls HIV effectively. Most people on treatment reach an undetectable viral load, meaning they can’t transmit HIV sexually and can expect a near-normal lifespan.
Nevirapine, one of the first NNRTI-class antiretrovirals, illustrates why genetics matter in HIV care. Current U.S. treatment guidelines no longer recommend nevirapine as standard adult therapy, largely due to liver toxicity and hypersensitivity risks. It still plays a role in newborn prophylaxis against mother-to-child transmission. Research has tied much of that side-effect risk to variations in the CYP2B6 gene, which controls how quickly the body breaks the drug down.
Can Genetic Testing Help Personalize HIV & AIDS Treatment?
In places, yes. Pharmacogenomic (PGx) testing looks at how your genes process medications, which can flag a risk before you fill a prescription. Two limits are worth stating first. PGx does not choose an antiretroviral regimen, and it cannot tell you whether your viral load will come down; that comes from resistance testing on the virus and from taking the medicine daily.
The one genetic test that must happen before an HIV prescription is HLA-B*57:01 before abacavir, and HLA-B is a separate test that is not on the RPh Labs panel. CYP2B6, the same gene tied to nevirapine metabolism, is among the 20 genes covered by RPh Labs’ Comprehensive PGx panel. The CLIA-certified, COLA-accredited test uses a simple cheek swab, no blood draw, and shows how your body may respond to 240+ medications across mental health, pain management, cardiology, and other specialties.
This kind of testing matters most for the harder-to-predict reactions, the rash, the liver enzyme spike, or the medication that simply doesn’t work, often discovered only after trial and error.
For anyone managing HIV alongside another chronic condition, like depression or chronic pain, knowing how your body metabolizes medications upfront can make treatment safer. Your doctor still makes the final call; the PGx report just gives them better information to work with.
How Can You Prevent HIV & Protect a Pregnancy From Transmission?
Prevention works at every stage, from avoiding exposure to protecting a baby during pregnancy.
- Use condoms consistently, and test regularly with new or multiple partners.
- Ask a doctor about PrEP if you’re at ongoing risk.
- Start PEP within 72 hours of a possible exposure.
- If you’re living with HIV, an undetectable viral load on ART means you can’t transmit it sexually (U=U).
For pregnancy, the CDC and WHO recommend ART throughout pregnancy, not a single dose at delivery. With consistent treatment, the risk of passing HIV to a baby drops below 1%, down from a substantially higher risk without any intervention. Higher-risk newborns may still receive short-term nevirapine or zidovudine after birth as extra protection.
Why hiv symptoms in women are often attributed to something else
Nothing on any list of hiv symptoms in women is unique to HIV. That is the core problem. The early signs of hiv overlap almost completely with common viral illnesses, and the later gynecologic patterns overlap with conditions most women have already had at some point.
So hiv symptoms in women tend to get treated one at a time. A recurring yeast infection gets an antifungal. Heavier periods get attributed to stress or a change in contraception. Fatigue gets blamed on work. Each explanation is reasonable on its own.
What changes the picture is a pattern rather than a single symptom, and that is true of hiv symptoms in men as well: infections that keep returning, that respond poorly to standard treatment, or that arrive alongside unexplained fatigue, night sweats or weight loss over months.
This is also why symptom watching is a poor substitute for testing. Many people have no noticeable illness at all during the years when the virus is most active. A test answers the question in days; the early signs of hiv never answer it at all.
If you are weighing whether to test, the simplest framing is that a negative result costs you one appointment and removes months of uncertainty, and a positive result found early is far more manageable than one found late.
The hiv testing window period, test by test
The hiv testing window period is the gap between a possible exposure and the point at which a test can reliably detect infection. Testing inside that gap is the most common reason people get a falsely reassuring result, whatever symptoms prompted the test.
Three types of test are in routine use, and they do not all detect infection at the same speed:
- Nucleic acid tests look for the virus itself and detect infection earliest, roughly 10 to 33 days after exposure. They are usually reserved for recent high-risk exposures or early symptoms.
- Lab antigen and antibody tests on blood drawn from a vein detect most infections around 18 to 45 days after exposure.
- Rapid finger-stick and oral fluid antibody tests, including home self-tests, have the longest hiv testing window period, roughly 23 to 90 days.
Because of that spread, a clinic may test you now and ask you to return later. That is not doubt about the first result; it is how the hiv testing window period is handled properly.
What a reactive result means
A reactive screening result is never the final answer. It is always confirmed with a second, different test before anyone is given a diagnosis. Screening tests are designed to be sensitive, which means a small number of reactive results turn out to be negative on confirmation. The hiv testing window period matters here too, because a very early infection can give a borderline result.
What an hiv rash looks like, and what else causes one
A rash is one of the more recognizable parts of early infection, which is why people search for it first. The hiv rash of acute infection is usually a scatter of small flat or slightly raised reddish spots on the chest, back, face or upper arms.
It is typically not very itchy, it appears along with other symptoms rather than alone, and it fades over one to two weeks without treatment. On darker skin the same rash often looks violet or darker brown rather than red, which is one reason it gets overlooked.
Plenty of other things produce a similar picture, including reactions to a new medicine, viral illnesses such as measles or roseola, secondary syphilis, and heat rash. An hiv rash by itself is weak evidence in either direction.
Two rash situations do need same-day attention regardless of cause: a rash with blistering, peeling skin, or sores in the mouth, eyes or genitals, and a rash that starts shortly after a new prescription. Both can signal a serious drug reaction.
An hiv rash that appears weeks after starting antiretroviral treatment is a different conversation again, since several antiretrovirals can cause rash themselves. Report it rather than stopping the medicine on your own, because some rashes are mild and some are not.
Hiv symptoms in men that get blamed on stress or aging
The article above lists the male-specific signs. The practical problem is that several hiv symptoms in men look exactly like ordinary midlife complaints, so they get absorbed into a story about work, sleep or getting older. That makes hiv symptoms in men easy to live with for years.
- Low energy, low libido and loss of muscle, which can reflect low testosterone rather than mood.
- Erection difficulties, which have many causes and are worth investigating rather than assuming.
- Slow-healing or recurring genital or anal sores, which often mean another sexually transmitted infection is present too.
- Rectal pain, discharge or urgency, which is treatable and frequently goes unmentioned out of embarrassment.
None of these prove anything on their own. What they justify is a full sexual health screen rather than treatment of one symptom in isolation, because infections cluster and finding one is a reason to look for others.
It is worth saying plainly that hiv symptoms in men are not limited to any group of men. Anyone who has had sex without a condom or shared injecting equipment can acquire HIV, and testing is a routine part of adult health care rather than an accusation.
If you are already being treated for another sexually transmitted infection, ask whether HIV testing is included. It often is not, unless someone asks.
Illnesses that mimic the early signs of hiv
During acute infection the immune system reacts, and that reaction feels like a bad flu. The early signs of hiv are therefore shared with several very common illnesses, which is why no clinician diagnoses from symptoms alone.
- Influenza and other respiratory viruses, which bring fever, aches and fatigue.
- Infectious mononucleosis, which classically causes sore throat, swollen glands and weeks of exhaustion.
- Streptococcal throat infection, which is treatable with antibiotics and easy to test for.
- Acute cytomegalovirus or toxoplasmosis, which can look almost identical to mononucleosis.
- Secondary syphilis, which can cause rash, fever and swollen glands and is also treatable.
The overlap cuts both ways. Assuming a flu-like illness must be HIV causes needless fear, and assuming it cannot be HIV causes missed diagnoses. A test settles it either way, and testing for several infections at once is usually simpler than testing for one. The early signs of hiv are not specific enough to sort out any other way.
One detail that does raise suspicion is timing. An illness like this two to four weeks after a specific unprotected exposure deserves a mention to the clinician you see, since it may change which test they order first.
Tell them about the exposure even if it feels awkward. The early signs of hiv are common enough that without that context, the sensible working diagnosis is usually something else entirely.
What to do in the first 72 hours after a possible exposure
This is the most time-sensitive information on this page, and the original article mentions it only in passing. Post-exposure prophylaxis, or PEP, is a short course of antiretroviral medicine that can prevent infection after an exposure has already happened.
It has to start as soon as possible and within 72 hours, whether or not you have any early signs of hiv. Sooner is better, and after 72 hours it is no longer offered for that exposure.
- Go to an emergency department, urgent care, sexual health clinic or your own clinician the same day. Say clearly that you may have been exposed to HIV and are asking about PEP.
- Bring what you know: roughly when the exposure happened, what kind it was, and anything you know about the other person’s status or treatment.
- Expect baseline testing for HIV and other infections before starting, which does not delay the first dose.
- Take the full course as prescribed, usually 28 days, and keep the follow-up testing appointments.
- Ask at that visit about PrEP, the medicine taken before exposure, if this is a risk that may come up again.
If sexual assault is involved, emergency departments have dedicated pathways that cover PEP, other infections, contraception and support services. You do not have to have decided anything about reporting to be seen and treated.
PEP is not the same as treatment, and it is not a substitute for testing later. Follow-up testing after the course is finished is what confirms the outcome.
The first few months after a diagnosis
A diagnosis today starts a fairly standard sequence, and knowing it in advance takes some of the fear out. Treatment is usually started quickly, often at the first or second visit, rather than waiting for the immune system to decline.
Early bloodwork typically includes a CD4 count, a viral load, kidney and liver function, hepatitis B and C screening, and a resistance test on your own virus. Some regimens also require a genetic test before the first dose, which is covered in the next section.
Whatever hiv symptoms in women or men led to the test, viral load is then rechecked over the following months to confirm it is falling, and most people reach an undetectable level within the first few months of consistent treatment. Undetectable on sustained treatment also means HIV is not passed to sexual partners.
Practical things worth asking about early
- Whether your state or county has a Ryan White program or AIDS Drug Assistance Program that helps with cost.
- Manufacturer copay assistance for the specific regimen you are prescribed.
- Who to call about side effects between appointments.
- How your records and results are kept, and who has access.
Side effects in the first weeks are common and often settle. Report them rather than stopping, because there are many effective combinations and switching is usually straightforward.
Where medication genetics helps, and where it does not
Pharmacogenomic testing has a real but narrow place in HIV care, and it is easy to overstate. It cannot detect HIV, cannot diagnose any condition, and cannot tell you whether the early signs of hiv you are worried about mean anything. It says nothing about the hiv testing window period either. It reports how your body is likely to process certain medicines.
Two genetic results actually change HIV prescribing:
- HLA-B*57:01 must be checked before abacavir, because people who carry it can have a severe hypersensitivity reaction. This gene is not on the RPh Labs 20-gene panel and is ordered separately by your clinician.
- CYP2B6 affects how quickly efavirenz and nevirapine are broken down, and slower metabolism is linked to higher drug levels and more side effects. CYP2B6 is on our panel, and CPIC publishes a guideline for it.
For the integrase inhibitor regimens most people now start, there is no routine gene test that changes the dose. Anyone implying otherwise is selling more than the science supports.
Where a panel does more work is everything else on the prescription list. People living with HIV are prescribed antidepressants, statins, acid reducers, pain medicines and clopidogrel like everyone else, and those are the classes with the strongest gene-guided dosing evidence. Our medication list by gene shows which drugs are reported.
If that sounds useful, the at-home cheek swab kit covers 20 genes against 240 or more medications, and every report is reviewed by a PharmD pharmacist. It is a prescribing aid you share with your clinician, not a test for any infection or disease.
Conclusion:
HIV symptoms vary widely between individuals, and between women and men. Testing, not symptom-watching, is the only reliable way to know your status. With modern, increasingly personalized treatment, long-term health is realistic for almost everyone diagnosed today.
RPh Labs’ at-home PGx testing kit helps you and your doctor make more informed medication decisions, for HIV-related care and 240+ other medications. Visit RPh Labs to learn more, or follow along on Facebook for ongoing updates on personalized medicine.
Disclaimer:
This article is for informational purposes only and doesn’t replace personalized medical advice. Talk to a healthcare provider about HIV testing, diagnosis, or treatment. Pictures in this blog are created using AI tools.
Hiv symptoms in women and men FAQ
What is HIV, and how is it different from AIDS?
HIV is the virus that attacks the immune system. AIDS, or stage 3 HIV, is the most advanced stage, diagnosed when CD4 counts fall below 200 or an opportunistic illness develops. Not everyone with HIV reaches AIDS, especially with early treatment.
How do you get HIV?
HIV spreads through specific body fluids, including blood, semen, vaginal fluid, and breast milk, usually through unprotected sex or shared needles. It doesn’t spread through saliva, sweat, or casual contact.
What are the first signs of HIV infection?
The first signs usually resemble the flu: fever, sore throat, fatigue, swollen lymph nodes, and a rash, appearing two to four weeks after exposure and fading within a few weeks.
How do you know if HIV has progressed to AIDS?
A doctor diagnoses AIDS through a CD4 count below 200 cells/mm³ or the presence of an AIDS-defining illness. Blood testing, not symptoms alone, confirms the stage.
Can you have HIV with no symptoms at all?
Yes. Many people feel completely healthy for years while HIV quietly damages the immune system, which is exactly why routine testing matters more than waiting for symptoms.
Is HIV treatable, and can people with HIV live a normal life?
Yes. Antiretroviral therapy controls HIV effectively. Most people on treatment live near-normal lifespans with an undetectable, untransmittable viral load.
How long is the hiv testing window period for a home test?
Home antibody tests have the longest window, roughly 23 to 90 days after exposure. A negative result early in that range does not rule infection out, so clinics usually repeat testing later. For a recent high-risk exposure, a lab test shortens the hiv testing window period compared with a self-test.
Can you tell an hiv rash apart from another rash by looking at it?
No. The acute rash is usually small flat reddish or darker spots on the chest, back or face that fade in one to two weeks, but drug reactions, other viruses and syphilis look similar. Any rash with blistering, peeling or mouth sores needs same-day care, whether or not an hiv rash is on your mind.
Do hiv symptoms in men and women appear at different times?
The acute flu-like phase is much the same for everyone, usually two to four weeks after exposure. The hiv symptoms in women that show up later reflect anatomy and hormones, such as recurring vaginal infections, and the later hiv symptoms in men reflect testosterone and prostate changes rather than a different timeline.
I have several early signs of hiv but no known exposure. What now?
See a clinician and ask for testing anyway, since HIV testing is recommended at least once for adults regardless of known risk. Mention every symptom and its timing, because look-alike illnesses such as mononucleosis, strep throat and syphilis are all treatable once identified.
Does a PGx test show whether I have HIV?
No. Pharmacogenomic testing looks at genes that affect how you process medicines. It does not detect infections, diagnose disease or predict future illness. Only an HIV test can tell you your status, and only after the hiv testing window period has passed, and your clinician orders HLA-B*57:01 separately when abacavir is being considered.



Leave a Reply